
The Kinect sensors, originally developed for gaming, have been used as a non-invasive approach to shoulder motion analysis. These sensors provide an image by detecting the pattern of projected infrared dots reflected by the body's surface. Processing these images against the computer's knowledge of human anatomy provides data on the position of defined body elements, such as the trunk, shoulder, arm, elbow and forearm. These measurements are observer independent and can be made in the clothed patient without the need to attach markers.

Several recent articles have presented the utility of such technology in understanding the relationship between shoulder motion and shoulder function.
In normal shoulders, range of motion correlates strongly with shoulder function,
Measurement of active shoulder motion using the Kinect, a commercially available infrared position detection system The active motion in well-functioning patient shoulders averaged 155° ± 22° abduction, 159° ± 14° flexion, 76° ± 18° external rotation in abduction, -59° ± 25° internal rotation in abduction, and -3.3 ± 3.7 inches of cross-body adduction, values similar to those obtained in normal volunteers. Use of the Kinect system proved practical in clinical examination rooms, requiring <5 minutes to document the 5 motions in both shoulders.

In arthritic shoulders, the range of motion is not the major determinant of shoulder function. In Relationship Between Patient-Reported Assessment of Shoulder Function and Objective Range-of-Motion Measurements, there was poor correlation between objective measurements of active abduction and total SST scores: the coefficients of determination (R) were 0.29 for the osteoarthritic shoulders of women and 0.25 for those of men. The authors concluded that factors other than active range of motion were the major drivers of the function of the arthritic shoulder.
In shoulders with cuff pathology, neither the range of motion or the extent of the pathology was the major determinant of shoulder function. In Patient self-assessed shoulder comfort and function and active motion are not closely related to surgically documented rotator cuff tear integrity the authors examined 55 shoulders having surgery for cuff-related symptoms, correlating the preoperative Simple Shoulder Test score with the preoperative active shoulder motion measured by the Kinect and with the integrity of the cuff observed at surgery. The 16 shoulders with tendinosis or partial-thickness tears had an average Simple Shoulder Test score of 3.7 ± 3.3, active abduction of 111° ± 38°, and active flexion of 115° ± 36°. The corresponding values were 3.6 ± 2.8, 94° ± 47°, and 94° ± 52° for the 22 full-thickness supraspinatus tears and 3.9 ± 2.7, 89° ± 39°, and 100° ± 39° for the 17 supraspinatus + infraspinatus tears.


The scapulothoroacic articulation is an important contributor to humerothoracic motion in patients having elective shoulder surgery. In The contribution of the scapula to active shoulder motion and self-assessed function in three hundred and fifty two patients prior to elective shoulder surgery, the Kinect system was used to assess active scapulothoracic (ST) and humerothoracic (HT) abduction in 12 controls and in 352 patients before elective shoulder surgery. For the controls, ST abduction averaged 26 ± 7° of the active HT abduction (135 ± 5°). For the 352 patients having elective surgery, active ST abduction averaged 12 ± 10° of the active HT abduction (72 ± 38). For 10 of the 12 SST functions, patients unable to perform the function had significantly less scapulothoracic abduction, for example, shoulders unable to lift one pound to shoulder level had 9 ± 8° of ST abduction in contrast to 17 ± 10° for those able to perform this function (p < .001).
While the information gathered using the Kinect remains clinically relevant, as pointed out by he authors of Reliability and agreement of Azure Kinect and Kinect v2 depth sensors in the shoulder joint range of motion estimation the original user-friendly Kinect systems are unfortunately no longer produced for game consoles. The Azure Kinect is available, but requires custom programming using the Azure Kinect Body Tracking SDK

Our hope is that developers will produce a "plug and play" product that can be used for shoulder clinical research and practice.
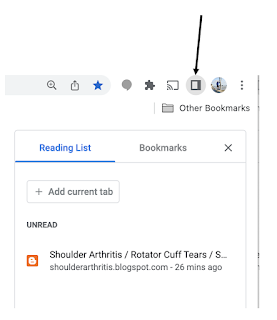
To add this blog to your reading list in Google Chrome, click on the reading list icon

You can support cutting edge shoulder research that is leading to better care for patients with shoulder problems, click on this link.
Follow on twitter: https://twitter.com/shoulderarth
Follow on facebook: click on this link
Follow on facebook: https://www.facebook.com/frederick.matsen
Follow on LinkedIn: https://www.linkedin.com/in/rick-matsen-88b1a8133/
Here are some videos that are of shoulder interestShoulder arthritis - what you need to know (see this link).How to x-ray the shoulder (see this link).The ream and run procedure (see this link).The total shoulder arthroplasty (see this link).The cuff tear arthropathy arthroplasty (see this link).The reverse total shoulder arthroplasty (see this link).The smooth and move procedure for irreparable rotator cuff tears (see this link).
Follow on twitter: https://twitter.com/shoulderarth
Follow on facebook: click on this link
Follow on facebook: https://www.facebook.com/frederick.matsen
Follow on LinkedIn: https://www.linkedin.com/in/rick-matsen-88b1a8133/


