Showing posts with label humeral component fixation. Show all posts

Saturday, June 27, 2026

How to choose a humeral component in shoulder arthroplasty: ASES Podcast 155


Hat's off to Drs Chalmers and Waterman for yet another outstanding ASES podcast: Episode 155, in which they were joined by Drs Athwal, Cuff and Hatzidakis to discuss fixation of humeral arthroplasty components: "standard" length stems (100-150 mm), short stems (60-90 mm) and stemless designs. 

Here are some takeaways from that presentation coupled with some additional thoughts from the U.W..

(1) The evolution in humeral components is attributed to (a) mitigation of complications (periprosthetic fracture, stress shielding from high canal-filling ratios, early loosening from certain ingrowth surfaces), (b) matching competitor features, and (c) responding to market forces.

The Standard Stem

(2) A standard length stem uses the canal as an alignment guide. It can be stabilized in the canal by (a) a bony ingrowth surface, (b) cement, or (c) reaming to a tight diaphyseal fit, reaming that, in any case, removes cortical bone asymmetrically and unpredictably. [7]. As discussed later in this post, the standard stem can also be stabilized in the canal by impaction grafting. Much of the stress-shielding literature conflates two different things — stem length and canal fill — and they are not the same. Proximal stress shielding tracks with the filling ratio — how much of the canal the implant occupies and how much load it diverts away from proximal bone — far more than with the absolute length of the stem. [9,10]. A long stem that fills the canal shields bone; a long stem that sits loosely in the canal, transferring load through impacted cancellous bone, need not. 

(3) Osteoporosis or altered humeral anatomy may drive the use of a longer stem for better fixation and durability.

The Short Stem

(4) The short stem depends on loading at the metaphyseal level — in bone of variable shape and quality — making both fixation and orientation challenging.

CT of the proximal humerus showing the thin metaphyseal cortex 


The short stem may not have enough leverage to reduce loosening.


Canal filling can lead to stress shielding


And periprosthetic fracture


The absence of the control provided by a standard length stem 
can lead to malpositioning of a short stem


(5) Stemless implants depend on fixation at the anatomic neck, where a thin cortical shell surrounds cancellous bone. Bone density at this level is of variable quality, especially in patients in the arthroplasty age range. While some surgeons claim “100% stemless,” that claim is not realistic for every patient having shoulder arthroplasty. 


AP radiograph with the anatomic-neck fixation zone annotated


The big question about stemless is how a surgeon decides, in a given patient, whether good fixation can be achieved. Preoperative imaging may give some clues, but it comes down to the intraoperative findings. Some have advocated the “thumb” test;


a more reliable approach is to insert the trial nucleus and determine whether it is solid. When it is not solid because of “mushy” cancellous bone, the options are limited. In our experience, adding cancellous graft at the anatomic neck does not rescue fixation: the site is already failing in cancellous bone, and loose graft packed against soft cancellous bone has nothing rigid to lock against. 
The ability to improve fixation with longer fins is likewise limited; upsizing the trial to gain purchase can risk the lateral cortex.
 

It is also worth noting that even when stemless fixation is achieved, adaptive bone changes are common; at short-to-mid term, however, they have not reliably correlated with loosening or worse function.[6,8]

So in the real world, the stemless-loving surgeon needs a Plan “B” when trial fixation is unstable. Conversion to a stemmed component is the most attractive option. One caveat: if the problem is mushy cancellous bone, fixation of a short stem can itself be challenging — a fatter stem versus bone graft, and the same question of how to assure durability in the desired position.

Avoiding Trouble with the Stemless

Be aware of common technical mistakes - assure complete head resection and avoid excessive varus or valgus. 

Insufficient head resection


Varus cut

The free-hand cut is key.

Revision

(6) Two concerns arise when the humeral component needs revision. First, removal of a well-fixed implant can risk fracture of the tuberosity, bone loss, and shaft fracture, and may require a humeral osteotomy or window. Second, although some humeral implants are “convertible” (the humeral fixation system stays in place), retaining the implant only makes sense if it is well fixed at an appropriate height and acceptable version. One podcast participant reported that 25–40% of nominally convertible stems cannot actually be converted in practice. Taken together, the routine use of “convertible” implants seems unattractive.


Malrotation


Too low or too high position of the stem


Another approach

(7) Our experience is that secure, safely revisable humeral component fixation can be achieved with a smooth, standard-length stem set at a small filling ratio and fixed with impaction autografting — using bone from the resected humeral head that one of our fellows named “God’s Own Glue” (see "Procrustean Method") [2,3]. The graft is impacted between a smooth stem and the endosteal cortex, where it stabilizes the implant at the time of surgery, rather than relying on a bony ingrowth surface, cement, or a tight diaphyseal press fit. [4]. A low filling ratio protects the humerus from stress shielding. Because the stem is deliberately undersized, load is transferred through grafted cancellous bone rather than bypassed down a canal-filling implant — addressing stress shielding at the variable that drives it. [9,10]. 

In 48 ream-and-run and 78 total shoulder arthroplasties using a smooth, standard-length impaction-grafted stem, two-year radiographs showed adaptive changes that were generally minor and not associated with component shift or subsidence. Inserted this way, a smooth standard-length stem offers secure, bone-preserving fixation providing results can serve as a basis for comparison for other component designs and fixation methods. [5]. 

In a consecutive single-surgeon series of 458 anatomic total shoulder arthroplasties using this construct (mean follow-up 9.2 years; 114 shoulders beyond ten years), Simple Shoulder Test scores improved from 3.3 to 9.2 and were sustained — never declining by more than the MCID — past ten years. The overall revision rate was 2.6% (12 of 458). None of the revisions were performed for a humeral-component cause: there was no humeral component loosening, no periprosthetic fracture, and no stem-related failure.[11] 


 A low filling ratio protects the humerus from stress shielding


Two year followup


Six year followup

Impaction grafting with a low filling ratio avoids incomplete seating of the humeral stem (humerus captivus)


Impaction grafting a standard stem in revising a failed short stem


Impaction grafting a thin long stem  in humeral deformity


Impaction grafting after fracture fixation


Impaction grafting a thin standard stem enables easy, safe removal followed by new implant insertion should revision be necessary.

Thus "revisability" does not require "convertibility"


Returning to the observation stated at the beginning of this post: humeral component evolution is attributed to (a) mitigation of complications, (b) matching competitor features, and (c) responding to market forces. 

Impaction grafting of a thin, smooth stem is an approach for addressing  periprosthetic fracture, stress shielding from high canal-filling ratios, and early loosening. It is not driven by market forces. Impaction grafting can be used with any standard length stem (anatomic or reverse) combined with freely available autograft from the patient’s own humeral head that would otherwise be discarded.


Should we be thinking straight?


Beauty in Simplicity

Tundra Swan
Union Bay Natural Area

Disclosure. The author has no financial relationship with any manufacturer of the orthopaedic devices discussed in this post.


References of interest

1. The ASES Podcast (American Shoulder and Elbow Surgeons), Episode 155: standard, short, and stemless humeral components and convertible designs. Available at: https://www.youtube.com/watch?v=q_s_g8oQgPg

2. Razfar N, Reeves JM, Langohr GDG, Willing R, Athwal GS, Johnson JA. Comparison of proximal humeral bone stresses between stemless, short stem, and standard stem length: a finite element analysis. J Shoulder Elbow Surg. 2016;25(7):1076–1083. doi:10.1016/j.jse.2015.11.011. PMID 26810016.

3. Reeves JM, Langohr GDG, Athwal GS, Johnson JA. The effect of stemless humeral component fixation feature design on bone stress and strain response: a finite element analysis. J Shoulder Elbow Surg. 2018;27(12):2232–2241. doi:10.1016/j.jse.2018.06.002. PMID 30104100.

4. Synnott S, Langohr GDG, Reeves JM, Johnson JA, Athwal GS. The effect of humeral implant thickness and canal fill on interface contact and bone stresses in the proximal humerus. JSES Int. 2021;5(5):881–888. doi:10.1016/j.jseint.2021.05.006.

5. Aibinder WR, Uddin F, Bicknell RT, Krupp R, Scheibel M, Athwal GS. Stress shielding following stemless anatomic total shoulder arthroplasty. Shoulder Elbow. 2023. doi:10.1177/17585732211058804. PMID 36895609.

6. Raiss P, Edwards TB, Deutsch A, Shah A, Bruckner T, Loew M, Boileau P, Walch G. Radiographic changes around humeral components in shoulder arthroplasty. J Bone Joint Surg Am. 2014;96(7):e54. doi:10.2106/JBJS.M.00378. PMID 24695931.

7. Denard PJ, Raiss P, Gobezie R, Edwards TB, Lederman E. Stress shielding of the humerus in press-fit anatomic shoulder arthroplasty: review and recommendations for evaluation. J Shoulder Elbow Surg. 2018;27(6):1139–1147. doi:10.1016/j.jse.2017.12.020. PMID 29422391.

8. Sheth MM, Kahsai EA, Yang J, Whitson AJ, Matsen FA III, Hsu JE. What is the clinical importance of radiographic changes around the humeral component in anatomic shoulder arthroplasty? A minimum 4-year follow-up study. J Shoulder Elbow Surg.2025;34(8):1877–1885. doi:10.1016/j.jse.2024.11.024. PMID 39800107.

9. Denard PJ, Hsu JE, Whitson A, Neradilek MB, Matsen FA III. Radiographic outcomes of impaction-grafted standard-length humeral components in total shoulder and ream-and-run arthroplasty: is stress shielding an issue? J Shoulder Elbow Surg.2019;28(11):2181–2190. doi:10.1016/j.jse.2019.03.016. PMID 31272887.

10. Kim SC, Park JH, Bukhary H, Yoo JC. Humeral stem with low filling ratio reduces stress shielding in primary reverse shoulder arthroplasty. Int Orthop. 2022;46(6):1341–1349. doi:10.1007/s00264-022-05383-4.

11. Lee M, Chebli C, Mounce D, Bertelsen A, Richardson M, Matsen FA III. Intramedullary reaming for press-fit fixation of a humeral component removes cortical bone asymmetrically. J Shoulder Elbow Surg. 2008;17(1):150–155. doi:10.1016/j.jse.2007.03.032. PMID 18029200.

12. Boorman RS, Hacker SA, Lippitt SB, Matsen FA III. A conservative broaching and impaction grafting technique for humeral component placement and fixation in shoulder arthroplasty: the Procrustean method. Tech Shoulder Elbow Surg.2001;2(3):166–175. doi:10.1097/00132589-200109000-00004.

13. Hacker SA, Boorman RS, Lippitt SB, Matsen FA III. Impaction grafting improves the fit of uncemented humeral arthroplasty. J Shoulder Elbow Surg. 2003;12(5):431–435. doi:10.1016/s1058-2746(03)00053-3. PMID 14564262.

14. Lucas RM, Hsu JE, Gee AO, Neradilek MB, Matsen FA III. Impaction autografting: bone-preserving, secure fixation of a standard humeral component. J Shoulder Elbow Surg. 2016;25(11):1787–1794. doi:10.1016/j.jse.2016.03.008. PMID 27262410.

15. Lee et al. Stress shielding effects of short stem alignment and bone density in reverse shoulder arthroplasty. J Orthop Res. 2026. doi:10.1002/jor.70140.

16. Vasiliadis AV, Giovanoulis V, Lepidas N, Bampis I, Servien E, Lustig S, Gunst S. Stress shielding in stemmed reverse shoulder arthroplasty: an updated review. SICOT J. 2024;10:37. doi:10.1051/sicotj/2024029.

17. Ritter D, Raiss P, Denard PJ, Werner BC, Müller PE, Woiczinski M, Wijdicks CA, Bachmaier S. Volumetric humeral canal fill ratio effects primary stability and cortical bone loading in short and standard stem reverse shoulder arthroplasty: a biomechanical and computational study. J Imaging. 2024;10(12):334. doi:10.3390/jimaging10120334.

18. Kramer M, Olach M, Zdravkovic V, Manser M, Raiss P, Jost B, Spross C. The effects of length and width of the stem on proximal humerus stress shielding in uncemented primary reverse total shoulder arthroplasty. Arch Orthop Trauma Surg. 2024. doi:10.1007/s00402-023-05129-w.

19. John PB, Nageswaran S. Mechanobiological evaluation of solid and multiple porous humeral stem architectures in reverse shoulder arthroplasty based on design and materials: a finite element study. Front Bioeng Biotechnol. 2026;13:1675726. doi:10.3389/fbioe.2025.1675726.

20. Takayama K, Ito H. Association between the canal filling ratio and bone resorption in trabecular metal stems in reverse total shoulder arthroplasty: a radiographic analysis using tomosynthesis. JSES Int. 2024;8(5):1077–1086. doi:10.1016/j.jseint.2024.05.010.


Saturday, November 29, 2025

Five stemless humeral arthroplasty components - design differences and regional humeral bone density

Stemless humeral arthroplasty depends on fixation of the humeral component to the proximal humeral metaphysis. The article referenced below maps the typical bone density of this region from the article Spatial mapping of humeral head bone density


Stemless components consist of (a) the humeral head and (b) a fixation device that connects the humeral head to the bone of the humeral metaphysis - we'll call that the "nucleus".

The first stemless humeral head component was the TESS (Total Evolutive Shoulder System), developed by Zimmer Biomet and introduced around 2004-2005. The TESS used a nucleus consisting of central peg with metaphyseal fins for fixation. 


The TESS had a relatively short clinical lifespan - it was discontinued after several years due to concerns about loosening and suboptimal outcomes. The device struggled with achieving reliable fixation, particularly in patients with poor bone quality.

In spite of this initial failure, many shoulder arthroplasty surgeons are currently successfully using newer stemless humeral components because of their ability to position the articular surface where the surgeon desires, rather than having it positioned as dictated by a humeral stem. 

For many patients the cancellous bone of the humeral metaphysis is sufficient for secure fixation of the implant. Thus, as long as the head cut is made properly and the bone is of good quality, things usually work out well.

The challenge is that in older patients or patients with diminished quality of the cancellous bone in the humeral metaphysis, the fixation may not be adequate.  

Some surgeons advocate preoperative CT imaging to examine local bone density. However, because the quality of fixation depends not only on bone quality but also on the design of the fixation device - the nucleus - that links the humeral head component to the humeral bone it seem more practical to insert the trial nucleus to assess fixation quality; if it's insufficient the surgeon can switch to a stemmed component.

Below I've endeavored to present five stemless shoulder arthroplasty systems arranged in chronological order of U.S. FDA clearance, examining their design philosophy, and mechanical advantages for osteoporotic bone quality. 

N.B. Please note that I have no conflict of interest with any of the companies selling these implants. Note also that I used Claude.ai to help in the analysis and preparation of this post. As such there may be errors and I'd welcome any evidence-based corrections/comments. Finally, this analysis does not present clinical outcome, radiographic followup data, or complexity of revision among these options - such a comparison would require a very large number of patients and careful control of bone density and surgical technique.

1. Simpliciti (Wright Medical/Stryker)

FDA CLEARANCE: March 10, 2015

Design Geometry

Three central fins (~10mm length) arranged in a star pattern with central contact through a nucleus. While the nucleus provides broad cancellous contact with minimal risk cortical perforation, the central fin placement relies on cancellous bone which is weaker in patients with diminished bone desitity. 

[Churchill RS et al. J Bone Joint Surg Am. 2016;98(7):552-560 (prospective two-year multicenter FDA IDE study, n=149). Churchill RS. J Shoulder Elbow Surg. 2014;23(9):1409-1414 (stemless shoulder arthroplasty current status review). First stemless system cleared in the United States, with clinical use in France beginning in 2010.]

2. Comprehensive Nano (Zimmer Biomet)

FDA CLEARANCE: April 2019


Design Geometry

Single central peg (15-20mm length, 8-10mm diameter) with tapered profile plus modular metaphyseal shells. Load concentrated in cancellous bone without peripheral bone engagement.

[Razmjou H et al. J Shoulder Elbow Surg. 2012;21(10):1-9 (early TESS/stemless design study). IDE study began with first U.S. implant in October 2013 at University of Virginia. Built on clinical heritage of Biomet T.E.S.S. stemless shoulder available in Europe since 2004. Comprehensive Nano IDE clinical trial data on file, Zimmer Biomet.]

3. Eclipse (Arthrex)

FDA CLEARANCE: August 1, 2019 (510(k) K183194)


Design Geometry

Fenestrated central screw (6.5mm diameter, 35mm length) penetrates into cancellous bone.  A collar-bearing baseplate is compressed against cancellous bone and the cortical rim.  The degree of compression depends on the purchase achieved by the screw in the central cancellous bone which can be weak.

Clinical Evidence

[Habermeyer P et al. J Shoulder Elbow Surg. 2015;24(9):1463-1472 (midterm results). Habermeyer P et al. JSES Open Access. 2019;3(4):234 (9-13 year results). Gallacher S et al. J Shoulder Elbow Surg. 2018;27(12):2191-2197 (independent 2-year study). Uschok S et al. J Shoulder Elbow Surg. 2017;26(2):225-232 (Eclipse vs Univers II RCT). Over 20,000 successful implantations in Europe and Canada prior to U.S. FDA clearance. Longest clinical track record of any stemless system (2005-present)].

4. CS EDGE (DJO/Enovis)

FDA CLEARANCE/LAUNCH: September 30, 2020

Design Geometry

Three peripheral serrated fins arranged in tripod configuration (~15mm length, 2-3mm thickness) plus a short central peg. Fins engage peripheral bone (greater tuberosity, calcar region). Insertion needs to avoid fin perforation of cortex.

Clinical Evidence

Product launch announcement September 30, 2020 (DJO/Enovis).  No published peer-reviewed clinical studies available to date.


5. OsseoFit (Zimmer Biomet)

FDA CLEARANCE: December 13, 2024

Design Geometry

Asymmetric 3-4 peripheral fins with variable lengths (12-18mm) scaled to engage the asymmetrical peripheral bone in humeal head. Posterior-inferior fin longest, medial fin engages calcar, superior fins engage greater tuberosity. Requires precise surgical technique for correct rotational alignment

Clinical Evidence

FDA clearance announcement December 13, 2024 (Zimmer Biomet). No published peer-reviewed clinical studies available to date.


Fundamental Principle: Humeral head bone architecture exhibits a shell-and-core structure with peripheral bone density significantly exceeding central metaphyseal bone quality, especially in elderly patients and those with osteoporosis. Peripheral fixation designs theoretically exploit the strongest available bone, while central fixation systems depend on the bone that may be compromised in typical arthroplasty candidates.


It's all about fixation


Acorn Woodpecker
Madera Canyon, AZ
2020


Follow on twitter/X: https://x.com/RickMatsen
Follow on facebook: https://www.facebook.com/shoulder.arthritis
Follow on LinkedIn: https://www.linkedin.com/in/rick-matsen-88b1a8133/

Here are some videos that are of shoulder interest
Shoulder arthritis - what you need to know (see this link).
How to x-ray the shoulder (see this link).
The ream and run procedure (see this link)
The total shoulder arthroplasty (see this link)
The cuff tear arthropathy arthroplasty (see this link).
The reverse total shoulder arthroplasty (see this link).
The smooth and move procedure for irreparable rotator cuff tears (see this link)
Shoulder rehabilitation exercises (see this link).


Sunday, February 19, 2023

A universal humeral component for anatomic shoulder arthroplasty?

There is a rapidly expanding number of humeral components being sold for anatomic arthroplasty. 

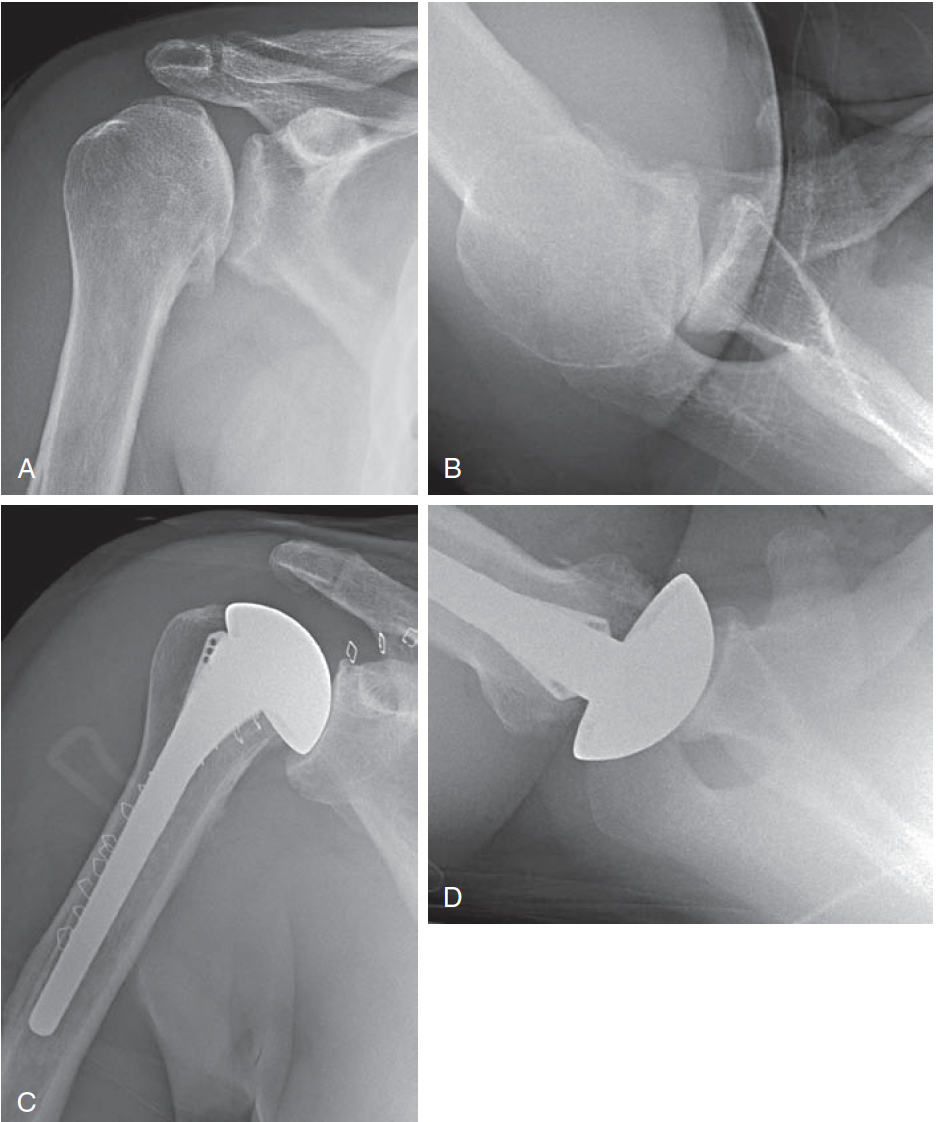
Let's consider the features of a legacy "universal" anatomic humeral component system against which these newer alternatives can be compared. 

The primary principles are (1) bone preservation, (2) avoidance of stress shielding, and (3) availability of humeral head options to manage the variations in arthritic pathoanatomy. 

These goals can be achieved with a standard length smooth stem with a low filling ratio fixed with impaction grafting coupled with a versatile selection of heads, including eccentric and cuff tear arthropathy options. NB: the author has no ties with any implant company, so this is not a sales pitch, but rather a perspective gained from almost 50 years of practice in shoulder arthroplasty.

Bone preservation: the head cut is the same as for short stemmed and stemless


Bone is not removed from the canal by reaming


instead, a stem diameter is selected that is smaller than the internal diameter of the diaphysis, yielding a small filling ratio without violating the bone of the canal.


The irregular internal anatomy of the humerus 

is fit to the stem using impaction grafting


The security of this fixation obviates the need for ingrowth surfaces on the implant, which can complicate removal of the stem should it become necessary.

The bone graft spreads the load broadly across the interface between the stem and bone minimizing the risk of stress shielding.


Stress shielding can be a problem when an implant is fit tightly against the distal cortical bone.


The use of a thin stem enables proper seating of the component
.


avoiding the issue of incomplete seating that can be seen with a large stem


Because the shaft is not weakened, the thin stem with impaction grafting technique minimizes the risk of intraoperative and postoperative fractures.


The thin stem with impaction grafting can be applied to special situations, for example when a plate is retained to protect the humerus.


The thin stem with impaction grafting technique can be safely applied to osteopenic bone, without being concerned about the results of the "thumb test"

or the need for intraoperative conversion from a stemless to a stemmed component (see Pre-operative Metaphyseal Cancellous Bone Density is Associated with Intraoperative Conversion to Stemmed Total Shoulder Arthroplasty).

A single piece body 


avoids the potential risk of corrosion, loosening and disassembly that can be an issue with mutlipart stems


Having the male taper on the head, rather than the body keeps it from blocking access to the glenoid


The prosthetic head should come in a wide variety of diameters of curvature to match different glenoid curvatures


Each head diameter of curvature should have different thicknesses 


so that the soft tissue tension can be adjusted to meet the 40, 50, 60 rules


 Eccentric / offset options should be available to manage excessive posterior translation


Extended articular surface options should be availabe to manage cuff tear arthropathy in CTA shoulders with retained active elevation.


These two non-anatomic strategies are difficult to accomplish with a stemless system.

Comment: There is a vast set of options available for the the humeral side of a glenohumeral arthroplasty. Surgeons seem to be switching from one to another to see which they like best. 
The challenge is to determine which, if any, are of greater value (benefit/cost) to the patient than the legacy approach presented above. Long term studies will be required, such as that presented by the population-based Australian Orthopaedic Association's National Joint Replacement Registry showing long term data for some of the options for treating primary osteoarthritis of the glenohumeral joint. Note the option that got gold.


You can support cutting edge shoulder research that is leading to better care for patients with shoulder problems, click on this link.

Follow on twitter: https://twitter.com/shoulderarth
Follow on facebook: click on this link
Follow on facebook: https://www.facebook.com/frederick.matsen
Follow on LinkedIn: https://www.linkedin.com/in/rick-matsen-88b1a8133/

Here are some videos that are of shoulder interest
Shoulder arthritis - what you need to know (see this link).
How to x-ray the shoulder (see this link).
The ream and run procedure (see this link).
The total shoulder arthroplasty (see this link).
The cuff tear arthropathy arthroplasty (see this link).
The reverse total shoulder arthroplasty (see this link).
The smooth and move procedure for irreparable rotator cuff tears (see this link).
Shoulder rehabilitation exercises (see this link).