Showing posts with label avascular necrosis. Show all posts

Wednesday, January 5, 2022

Forty year old man with severe arthritic deformity

 An active man with systemic lupus presented with pain and stiffness of his right shoulder. He could perform only four of the 12 Simple Shoulder Test functions with his right shoulder.

His x-rays showed collapse of the humeral head from avascular necrosis with secondary arthritis and humeral head deformity.


We discussed the options of a hemiarthroplasty and an anatomic total shoulder arthroplasty. At surgery, exposure was difficult - an in situ head cut was required to expose the humerus. Even after soft tissue releases, there was insufficient room in the joint for a glenoid component. The glenoid articular surface was smoothed with a curette. A standard length humeral stem was fixed with impaction autografting.

After surgery, we had difficulty regaining motion in spite of the patient's great efforts at therapy. Over the first year, three manipulations under anesthesia were carried out.

At 14 months after his procedure, he returned to have his opposite (left) side done. He was pleased with the comfort and function of his right shoulder and was able to answer "yes" to all 12 functions of the Simple Shoulder Test. The function of both shoulders is shown below.

His right shoulder x-rays at 14 months post op are shown below.


The preoperative films of his left shoulder are shown here.


A similar procedure is planned for this shoulder, anticipating the need for another major effort to regain his lost motion.

Comment: This case demonstrates a conservative surgical approach to a severely arthritic shoulder in a young patient. It showed us that post-arthroplasty manipulation(s) can be helpful in regaining motion of a shoulder that has been chronically stiff.

Follow on facebook: https://www.facebook.com/frederick.matsen

Follow on LinkedIn: https://www.linkedin.com/in/rick-matsen-88b1a8133/


How you can support research in shoulder surgery Click on this link.

Here are some videos that are of shoulder interest
Shoulder arthritis - what you need to know (see this link)
Shoulder arthritis - x-ray appearance (see this link)
The smooth and move for irreparable cuff tears (see this link)
The total shoulder arthroplasty (see this link).
The ream and run technique is shown in this link.
The cuff tear arthropathy arthroplasty (see this link).
The reverse total shoulder arthroplasty (see this link).

Monday, September 13, 2021

44 year old with severe humeral head collapse from avascular necrosis

 A 44 year old patient who had been treated for lupus with high dose steroids presented with pain and loss of motion of the right shoulder and these x-rays showing avascular necrosis with proximal humeral deformity.


After discussion of the options, he elected a hemiarthoplasty without glenoid arthroplasty.

Here are his films at 7 months when he presented requesting the same procedure on the contralateral shoulder for a similar deformity.

On examination he demonstrated 140 degrees of comfortable active elevation. 


It is hoped that this will provide a durable solution for a severe deformity in a young man.


Follow on twitter: https://twitter.com/shoulderarth

Follow on facebook: https://www.facebook.com/frederick.matsen

Follow on LinkedIn: https://www.linkedin.com/in/rick-matsen-88b1a8133/


How you can support research in shoulder surgery Click on this link.

Here are some videos that are of shoulder interest
Shoulder arthritis - what you need to know (see this link)
The smooth and move for irreparable cuff tears (see this link)
The total shoulder arthroplasty (see this link).
The ream and run technique is shown in this link.
The cuff tear arthropathy arthroplasty (see this link).
The reverse total shoulder arthroplasty (see this link).

Shoulder rehabilitation exercises (see this link).

Wednesday, September 9, 2020

Avascular necrosis in a patient under 40 years of age

 A young man present with incapacitating pain in his left shoulder.

His plan films and MRI show a small central area of avascular necrosis. No risk factors for AVN were identified.


After discussion of the alternatives of non-operative management, debridement, drilling the defect, a partial prosthetic surface replacement, an allograft and a hemiarthroplasty, the patient elected the latter.

At surgery the glenoid articular cartilage was intact. A central defect in the humeral head was seen
with a loose flap of cartilage
An anatomic hemiarthroplasty was performed under general anesthesia without a brachial plexus block using a canal-sparing smooth stemmed humeral component inserted with impaction autografting.


On the evening of surgery he had excellent comfortable range of motion.


Comment: While other options were considered, a robust anatomic hemiarthroplasty was selected to provide a durable return to high levels of activity.

To subscribe to this blog, enter your email in the box to your right that looks like the below


===
How you can support research in shoulder surgery Click on this link.

We have a new set of shoulder youtubes about the shoulder, check them out at this link.

Be sure to visit "Ream and Run - the state of the art" regarding this radically conservative approach to shoulder arthritis at this link and this link

Use the "Search" box to the right to find other topics of interest to you.

You may be interested in some of our most visited web pages  arthritis, total shoulder, ream and runreverse total shoulderCTA arthroplasty, and rotator cuff surgery as well as the 'ream and run essentials'

Thursday, November 28, 2019

Severe post traumatic arthritis managed with a ream and run

A very active man in his 50s sustained a traumatic posterior fracture dislocation.


This was treated with open reduction internal fixation. An anatomic reconstruction was achieved. The patient achieved excellent function.
 At a year after surgery the shoulder became painful and showed early signs of avascular necrosis as shown below.

Two years after surgery, the humeral head had completely collapsed.

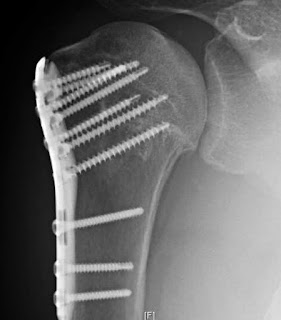
 The axillary "truth" view shows screws penetrating the collapsed head and eroding the glenoid. His shoulder had essentially no motion at the glenohumeral joint.

Because of his active lifestyle, he elected to have a ream and run procedure. At surgery his humeral head looked like this.

The procedure was performed without a brachial plexus block. His biceps tendon was preserved.
His immediate postoperative films are shown below.


The axillary "truth" view shows his humeral head centered on the reamed glenoid.

On the morning after surgery he had regained excellent assisted motion as shown below.


It is most encouraging to see the early restoration of movement. This motivated patient should be able to maintain his motion with at home exercises.

After discharge on the second postoperative day he took his exercises outdoors


To see a YouTube video on how the ream and run is done, click on this link.

=====
To see our new series of youtube videos on important shoulder surgeries and how they are done, click here.

Use the "Search" box to the right to find other topics of interest to you.


You may be interested in some of our most visited web pages  arthritis, total shoulder, ream and runreverse total shoulderCTA arthroplasty, and rotator cuff surgery as well as the 'ream and run essentials'

Monday, October 31, 2016

Avascular necrosis: to decompress or not to decompress

Core decompression and arthroplasty outcomes for atraumatic osteonecrosis of the humeral head

These authors evaluated the radiographic and functional outcomes after procedures for two forms of humeral head atraumatic avascular necrosis (HAAVN):
(1) chronic steroid-induced(CSI) 12 cases  and 
2) sickle cell disease (SCD) 13 cases. 
Patients with post traumatic AVN were excluded.

11 shoulders (stage I/II disease) underwent core decompression. Seven of 8 shoulders (88%) progressed to stage III/IV after decompression. All SCD patients progressed to collapse. 

19 shoulders had surface replacement, hemiarthroplasty, or TSA. 13 of 16 arthroplasty patients (81%) had satisfactory to excellent results. One surface replacement was revised to a reverse TSA.

The improvement in the Simple Shoulder Test Scores for the arthroplasty patients were comparable to the improvement seen with other pathologies. On average, patients improved from an SST of 2 preoperatively to 10 at year one and year two.

They concluded that core decompression for AVN in SCD patients does not alter osteonecrosis progression or humeral head collapse; shoulder arthroplasty was their preferred treatment for stages III, IV and V. 

Comment: In our experience patients with AVN of the shoulder related to sickle cell disease have high levels of pain (in spite of seemingly mild radiographic changes) and often have multiple sites of involvement. For these reasons - in addition to the progression of disease after decompression - we often discuss with the patient the alternative of a total shoulder arthroplasty to maximize the changes of improving their comfort and function.


Thursday, May 12, 2016

Avascular necrosis of the humeral head - natural progression

A man presented with the atraumatic onset of right shoulder pain. He had no history of excess alcohol use or steroid use other than three injections. Here are a series of images that show the progression of his AVN (see link here and here).
August 2013
Essentially normal x-ray

February 2015
Some sclerosis of the superior medial humeral articular surface

 February 2015
MRI showing subsurface crack in the humeral head

February 2016
Early collapse of the avascular segment


May 2016
Surgical photo showing break in articular surface


May 2016
Corss section showing crack beneath joint surface


May 2016
Impaction grafted hemiarthroplasty selected because of retained glenoid articular cartilage


===
Consultation for those who live a distance away from Seattle.

Check out the new Shoulder Arthritis Book - click here.

Click here to see the new Rotator Cuff Book

To see the topics covered in this Blog, click here

Use the "Search" box to the right to find other topics of interest to you.

You may be interested in some of our most visited web pages including:shoulder arthritis, total shoulder, ream and runreverse total shoulderCTA arthroplasty, and rotator cuff surgery as well as the 'ream and run essentials'


Monday, April 18, 2016

Avascular necrosis of the humeral head in sickle cell disease - to decompress or not to decompress?

Core decompression and arthroplasty outcomes for atraumatic osteonecrosis of the humeral head

These authors evaluated radiographic and functional outcomes after procedures for humeral head atraumatic avascular necrosis (HAAVN), decompression efficacy in sickle cell disease (SCD) populations, and report outcomes of advanced disease requiring arthroplasty. The condition was staged according to the system of Cruess:

• Stage I was defined by radiographs showing no abnormalities and only marrow signal changes on MRI.

• Stage II disease was marked by wedged or mottled sclerosis on plain films but overall maintained sphericity of the humeral head.

• Stage III was identified by subchondral fracturing with frequently associated crescent sign signifying this compromised chondral integrity.

• Stage IV showed further subchondral bone collapse and flattening, with marked loss of humeral head sphericity on plain films.

• Stage V, the final stage of AVN, showed humeral head collapse along with significant deformation and extension of erosion into the glenoid.

Stage I/II disease received core decompression and ultrasound bone stimulation. Stage III received surface replacement or hemiarthroplasty, and arthroplasty was performed for stage IV/V.

Seven of 8 shoulders (88%) progressed to stage III/IV after decompression. All SCD patients progressed to collapse.

19 shoulders had a surface replacement, hemiarthroplasty, or TSA.  13 of 16 arthroplasty patients (81%) had satisfactory to excellent results. One surface replacement was revised to reverse TSA.

The authors concluded that core decompression for AVN in SCD patients does not alter osteonecrosis progression and humeral head collapse. Resurfacing and hemiarthroplasty are viable treatment options for stage III, whereas shoulder replacement for stage IV/V disease appears to offer better functional results.

Comment: This article points to poor results from core decompression in sickle cell disease. The role of core decompression for early stage avascular necrosis from other etiologies remains unclear.

===


Check out the new Shoulder Arthritis Book - click here.


Use the "Search" box to the right to find other topics of interest to you.

You may be interested in some of our most visited web pages including:shoulder arthritis, total shoulder, ream and runreverse total shoulderCTA arthroplasty, and rotator cuff surgery as well as the 'ream and run essentials'


Sunday, September 13, 2015

Shoulder arthroplasty for atraumatic osteonecrosis - not that simple.

Shoulder arthroplasty for atraumatic osteonecrosis of the humeral head

These authors reported on 67 hemiarthroplasties and 71 total shoulder arthroplasties that they performed for atraumatic osteonecrosis and observed for at least 2 years (mean, 9.3 years) or until reoperation. 71% of the patients were female. The average patient age for the hemiarthroplasties was 48 years and 64 for the total shoulder arthroplasties. In 79 of the cases, the osteonecrosis was attributed to steroid use and in 38 the cause was not identified. Hemiarthroplasty was elected if the glenoid was covered with articular cartilage or if the patient 'wanted an extremely active lifestyle.'

Twenty-five percent of glenoid components were determined to be at risk at a mean follow-up of only 6.7 years.  At a mean follow-up of 6.6 years, 7 shoulders having hemiarthroplasty (14%) had moderate or severe glenoid erosion.

The revision free survivorship is shown in the chart below.


Eight hemiarthroplasties and 11 total shoulders underwent reoperation. The most common cause for reoperation was painful glenoid arthrosis in the HA group and aseptic loosening in the TSA group. 

There were no operative complications in the hemiarthroplasty group. Ten total shoulders experienced complications. Intraoperative fractures occurred in 3 shoulders. Two of these were greater tuberosity fractures repaired with suture fixation. The third was a fracture at the tip of the humeral stem treated with conversion to a longer stem. Two shoulders had postoperative neurapraxias that resolved completely. One shoulder was treated for a superficial postoperative infection with oral antibiotics. One patient experienced a postoperative hematoma that resolved
with observation. Three shoulders developed clinically significant subluxation (2, anterior; 1, posterior). The reasons for these different complication rates are not understood.

Hemiarthroplasty yielded 31 excellent, 14 satisfactory, and 22 unsatisfactory results. Total shoulder arthroplasty yielded 30 excellent, 19 satisfactory, and 22 unsatisfactory results. These results are summarized in the chart below.
The major reasons for unsatisfactory results were reoperation, pain, loss of motion, and subjective dissatisfaction.

Comment: Osteonecrosis can exist in a wide range of severities as shown in the figures from our collection. Note the differences in the extent of head involvement, the degree of collapse and the involvement of the glenoid.


Patients with this diagnosis have a range of conditions that may have prompted the use of corticosteroids - from asthma to rejection of a renal transplant. 

It can be easily seen that there are major differences in the patients having hemiarthroplasty and those having total shoulders. This would have been a more informative study if the methods had been based on a multivariate analysis of the factors affecting (a) survivorship and (b) clinical outcome, including patient age, sex, underlying disease, degree of collapse, degree of head involvement, degree of glenoid involvement, and type of arthroplasty. In that way we could better understand the factors associated with better and worse results.

Friday, September 6, 2013

Avascular necrosis of the shoulder, x-ray appearance

Avascular necrosis is a condition in which the blood supply to the humeral head is compromised, resulting in death and eventual collapse of the humeral joint surface. Common contributing factors are steroid medications, alcoholism, fracture, prior surgery and inflammatory joint disease. A typical case is shown here. And here is another.

As we've emphasized before (see here), two plain x-rays are necessary and sufficient to make most diagnoses of shoulder arthritis.

Here is an anteroposterior (AP) and an axillary view typical of shoulders with avascular necrosis.

The upper view, the AP shows complete collapse of the humeral head with minimal glenoid deformity.


The standardized axillary view reveals much more of the pathology: glenoid is convex and the concave humeral head is collapsed around it.


You can support cutting edge shoulder research that is leading to better care for patients with shoulder problems, click on this link.

Follow on twitter: https://twitter.com/shoulderarth
Follow on facebook: click on this link
Follow on facebook: https://www.facebook.com/frederick.matsen
Follow on LinkedIn: https://www.linkedin.com/in/rick-matsen-88b1a8133/

Here are some videos that are of shoulder interest
Shoulder arthritis - what you need to know (see this link).
How to x-ray the shoulder (see this link).
The ream and run procedure (see this link).
The total shoulder arthroplasty (see this link).
The cuff tear arthropathy arthroplasty (see this link).
The reverse total shoulder arthroplasty (see this link).
The smooth and move procedure for irreparable rotator cuff tears (see this link).
Shoulder rehabilitation exercises (see this link)

Tuesday, January 1, 2013

What is arthritis? What is the treatment for shoulder arthritis?


Our joints are normally covered by smooth articular cartilage.


When two normal joint surfaces rub on each other, the friction is less than that of an ice skate on ice.


In most cases, a person's joint cartilage lasts their whole life long.

However, certain conditions can destroy the smooth functioning of the joint. The shoulder can be affected by different types of arthritis

The traditional dictionary definition of "arthritis" is "inflammation of a joint, usually accompanied by pain, swelling, and stiffness". This definition applies to conditions such as rheumatoid arthritispsoriatic arthritislupusgoutankylosing spondylitiscrystal deposition diseaseReiter'slyme diseasejuvenile arthritisinfectious (septic) arthritis, and Sjogren's in which inflammation of the joint lining, or synovium, forms a pannus which invades the articular cartilage normally covering the joint.

Today many of these conditions can be managed with medications before the cartilage is lost.

The more common types of 'arthritis' of the shoulder are not the result of inflammation at all, but rather represent the non-inflammatory loss of cartilage from wear (osteoarthritis (degenerative joint disease)) , injury (post traumatic arthritis), complications of surgery (chondrolysispost-arthroscopic glenohumeral chondrolysiscapsulorrhaphy arthropathy) or association with rotator cuff loss ( cuff tear arthropathy). 

In such cases, the cartilage is destroyed without inflammation, leaving a rough joint surface.


When the shoulder joint reaches this stage, the degree of loss can be seen on x-ray. If symptoms are limiting the quality of life and if gentle exercises are not effective, consideration can be given to a total shoulder replacement or, in selected cases, to a ream and run procedure. In rarer situations a reverse total shoulder or a CTA arthroplasty may be the best choice. The role of surgeon experience is discussed here.

We have posted 67 articles to help individuals with arthritis on our living with arthritis page, including tips on preserving the quality of life. Here are some tips on living well with arthritis.

--

Use the "Search" box to the right to find other topics of interest to you.

You may be interested in some of our most visited web pages including:shoulder arthritis, total shoulder, ream and runreverse total shoulderCTA arthroplasty,  and rotator cuff surgery.