Showing posts with label comfort. Show all posts

Wednesday, October 12, 2022

Rotator cuff tears - what determines the patient's comfort and function?

The symptoms experienced by patients with rotator cuff pathology vary widely, ranging from asymptomatic to disabling (see Asymptomatic Rotator Cuff Tears). In A prospective multipractice investigation of patients with full-thickness rotator cuff tears: the importance of comorbidities, practice, and other covariables on self-assessed shoulder function and health status the authors found that shoulder function of patients with cuff tears was correlated with medical and social comorbidities. 

In a study of 191 patients with full thickness cuff tears, the authors of A prospective, multipractice study of shoulder function and health status in patients with documented rotator cuff tears  found that shoulder function was significantly correlated with  patient sex, involvement of the infraspinatus tendon and workers’ compensation claims. 

The authors of Patient self-assessed shoulder comfort and function and active motion are not closely related to surgically documented rotator cuff tear integrity found that the extent of the cuff tear was poorly associated with the shoulder's comfort or function. 


A systematic review, Are Psychosocial Factors Associated With Patient-reported Outcome Measures in Patients With Rotator Cuff Tears? found that lower emotional and mental health function was associated with greater pain, disability and lower physical function in patients with cuff tears.


The authors of Psychological distress negatively affects self-assessment of shoulder function in patients with rotator cuff tears found that higher levels of psychological distress are associated with inferior patient self-assessment of shoulder pain and function using the VAS, the Simple Shoulder Test, and the American Shoulder and Elbow Surgeons score.


Depression may drive patients to have evaluation and treatment for cuff disorders as suggested by the authors of Depression increases the risk of rotator cuff tear and rotator cuff repair surgery: a nationwide population-based study. who found that a diagnosis of cuff tear and the incidence of rotator cuff repair surgery was greater in patients with depression. Depressed patients also had a significantly increased risk of subsequent rotator cuff repair surgery.


Recently, the authors of Rotator cuff tendinopathy: magnitude of incapability is associated with greater symptoms of depression rather than pathology severity again pointed out that while rotator cuff tendinopathy develops in most persons during their lifetimes, it is often accommodated, and that there is limited correspondence between symptom intensity and pathology severity. 


They studied the relative association of functional capability with symptoms of anxiety or depression and with quantifications of rotator cuff pathology such as defect size, degree of retraction, and muscle atrophy among 71 adults seeking specialty care for symptoms of rotator cuff tendinopathy who had a recent shoulder MRI and completed the following questionnaires: 

1.Patient-Reported Outcomes Measurement Information System (PROMIS) Global Health questionnaire (a measure of symptom intensity and magnitude of

capability, consisting of mental and physical health subscores), 

2. Generalized Anxiety Disorder (GAD) questionnaire (measuring symptoms of anxiety), and 

3. Patient Health Questionnaire (PHQ) (measuring symptoms of depression). 


Muscle atrophy was assessed based on oblique-sagittal plane MRI images medial to

the coracoid process according to the system of Warner et al with conversion to a 4-point numeric scale. Grade 0 (no atrophy) was assigned when the muscle completely filled its fossa and there was a convex extension out of the fossa; grade 1 (mild atrophy), when the muscle filled the fossa and the outer contour was flat with respect to the fossa; grade 2 (moderate atrophy), when the muscle was concave with respect to the fossa; and grade 3 (severe atrophy), when the muscle was barely apparent in the fossa.


They found the magnitude of incapability among patients seeking care for rotator cuff pathology was associated with symptoms of depression but not with the severity of the rotator cuff pathology.


Comment: Taken together these studies suggest that the symptoms and degree of disability experienced by patients with rotator cuff tears is strongly influenced by factors other than the magnitude of the cuff pathology. Such factors may include coverage by workers' compensation insurance, patient sex, social well being and mental health. These same factors may influence the tipping point for rotator cuff repair surgery and may have negative effects on the outcome of this procedure as well.


To add this blog to your reading list in Google Chrome, click on the reading list icon


You can support cutting edge shoulder research that is leading to better care for patients with shoulder problems, click on this link.


Follow on twitter: https://twitter.com/shoulderarth

Follow on facebook: click on this link

Follow on facebook: https://www.facebook.com/frederick.matsen

Follow on LinkedIn: https://www.linkedin.com/in/rick-matsen-88b1a8133/

Here are some videos that are of shoulder interest
Shoulder arthritis - what you need to know (see this link).
How to x-ray the shoulder (see this link).
The ream and run procedure (see this link).
The total shoulder arthroplasty (see this link).
The cuff tear arthropathy arthroplasty (see this link).
The reverse total shoulder arthroplasty (see this link).
The smooth and move procedure for irreparable rotator cuff tears (see this link).
Shoulder rehabilitation exercises (see this link).


Monday, May 3, 2021

What determines the preoperative comfort and function of patients coming for shoulder arthroplasty?

Associations of preoperative patient mental health status and sociodemographic and clinical characteristics with baseline pain, function, and satisfaction in patients undergoing primary shoulder arthroplasty

These authors hypothesized that worse mental health status assessed by the Veterans RAND 12-Item Health Survey (VR-12) mental component score (MCS), glenoid bone loss, and increasing rotator cuff tear severity would be associated with lower values for the preoperative shoulder comfort and function as reflected by the Penn Shoulder Score in 788 patients having shoulder arthroplasty. 


They found that the following factors were statistically significantly associated with lower total scores for preoperative comfort and function: a lower VR-12 MCS, fewer years of eduction, female sex, and preoperative opiod use. Interestingly, shoulder characteristics, such as prior surgery, glenoid bone loss, and rotator cuff status did not have statistically significant associations with preoperative comfort and function in either omnibus tests or in Bonferroni-Holm adjusted pair-wise comparisons for trichotomous variables.


Comment: The lack of significant relationship between the severity of shoulder pathoanatomy and preoperative comfort and function was also noted by another recent article Prearthroplasty glenohumeral pathoanatomy and its relationship to patient’s sex, age, diagnosis, and self-assessed shoulder comfort and function in which the individuals with higher grades of shoulder pathology had better preoperative comfort and function (see below).


It appears that patient factors rather than shoulder factors are the primary determinants of preoperative shoulder comfort and function.


It seems likely that the same patient factors (lower VR-12 MCS, fewer years of eduction, female sex, and preoperative opiod use) may have strong effects on the comfort and function after shoulder arthroplasty. 


Here are some videos that are of shoulder interest
Shoulder arthritis - what you need to know (see this link).
How to x-ray the shoulder (see this link).
The ream and run procedure (see this link).
The total shoulder arthroplasty (see this link).
The cuff tear arthropathy arthroplasty (see this link).
The reverse total shoulder arthroplasty (see this link).
The smooth and move procedure for irreparable rotator cuff tears (see this link).
Shoulder rehabilitation exercises (see this link).


Wednesday, October 12, 2016

Rotator cuff tears - comfort and function are unrelated to cuff integrity in asymptomatic shoulders

Prevalence of asymptomatic rotator cuff tear and their related factors in the Korean population.

These authors investigated 486 volunteers (70.4% female; mean age, 53.1; range, 20-82 years) without any shoulder symptom complaints. Background data, medical history, clinical self-assessment, and physical examination were recorded.

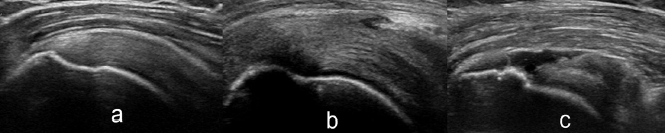
Cuff integrity was evaluated by ultrasound.Below are the ultrasound images of an intact cuff (a), partial tear (b), and full thickness tear (c).


Full thickness tears (FTRCT) were found in 23 subjects (4.7%) but only in those aged ≥49 years. Subjects aged 50-59, 60-69, and ≥70 years of age had FTRCT prevalence rates of 3.5%, 13.3%, and 11.1%, respectively. The prevalence of FTRCTs was higher in subjects with diabetes (P = .042) and a smoking history (P= .002), but no differences were noted for the presence of thyroid disease (P = .051).

The comfort and function of the shoulders were essentially independent of the cuff integrity (data from authors' Table V):


Comment: In this series of 486 volunteers without any shoulder complaints, the comfort and function were not affected by the integrity of the cuff. This again points to the observation that full and partial thickness cuff tears can be asymptomatic.

===

Monday, March 21, 2011

The SST in tracking recovery of comfort and function after shoulder reconstruction, for example after a ream and run procedure.

One of the operations we offer to patients with shoulder arthritis is the ream and run procedure. We will discuss this operation more in subsequent posts, but in brief it is a method of shoulder joint replacement arthroplasty that avoids the potential risks associated with a plastic socket.
The chart above shows how the Simple Shoulder Test (SST) is used to document the recovery of patient self-assessed comfort and function after a ream and run procedure for shoulder arthritis. The data represent the average recovery from a consecutive series of over 100 patients with at least two years of post surgical follow-up. The vertical axis represents the total number of SST questions answered 'yes', while the horizontal axis represents the years after surgery. The dots show individual data points and the lines show the average (plus or minus one standard deviation) for all the patients.
Since, on average, patients having the ream and run live over 500 miles from our center, routine office visits are impractical for them.  Because patients mail or email their results to us, we have been able to keep close tabs on their recovery using the Simple Shoulder Test.

The full article was recently published in the JBJS and discussed in this post.
--


=====
We have a new set of shoulder youtubes about the shoulder, check them out at this link.

Be sure to visit "Ream and Run - the state of the art" regarding this radically conservative approach to shoulder arthritis at this link and this link

Use the "Search" box to the right to find other topics of interest to you.


You may be interested in some of our most visited web pages arthritis, total shoulder, ream and run, reverse total shoulder, CTA arthroplasty, and rotator cuff surgery as well as the 'ream and run essentials'

Sunday, March 20, 2011

An example, the SST in Degenerative Joint Disease of the Shoulder

To illustrate the way in which the  Simple Shoulder Test (SST) characterizes the status of the shoulder, here are the average SST results from over 2000 patients that came to us for total shoulder replacement for arthritis. Keep in mind that this represents the patients' assessment of their own shoulders. It serves as the starting point for treatment and for measuring the effectiveness of the treatment selected.


--
=====
We have a new set of shoulder youtubes about the shoulder, check them out at this link.

Be sure to visit "Ream and Run - the state of the art" regarding this radically conservative approach to shoulder arthritis at this link and this link

Use the "Search" box to the right to find other topics of interest to you.


You may be interested in some of our most visited web pages arthritis, total shoulder, ream and run, reverse total shoulder, CTA arthroplasty, and rotator cuff surgery as well as the 'ream and run essentials'

Saturday, March 19, 2011

The Simple Shoulder Test

The goal of treating a person with a shoulder problem is to improve his or her  comfort and function. With this purpose in mind, we developed the Simple Shoulder Test (SST) to enable each individual to evaluate each of their shoulders in their own terms before and sequentially after treatment. The SST, as it has come to be known, is convenient for both the patient and the doctor - it can be completed at home and emailed in to the doctor's office - so that the course of the shoulder can be followed for long periods of time. The SST is now used in many languages the word over as a 'universal currency' by which patients, shoulder conditions, and results of different treatments can be compared.  This simple tool enables orthopaedic surgeons to achieve long term follow-up on the course of recovery and the durability of different approaches to reconstruction of the arthritic shoulder. The abstract of one of our early publications using the SST is shown below.

The Simple Shoulder Test

Name _________________                       


Date this form is completed: ________

Please answer YES or NO for BOTH of your shoulders
RIGHT
LEFT


YES
NO
YES
NO
1
Is your shoulder comfortable with your arm at rest by your side?
£
£
£
£
2
Does your shoulder allow you to sleep comfortably?
£
£
£
£
3
Can you reach the small of your back to tuck in your shirt with your hand?

£
£
£
£
4
Can you place your hand behind your head with the elbow straight out to the side?
£
£
£
£
5
Can you place a coin on a shelf at the level of your shoulder without bending your elbow?
£
£
£
£
6
Can you lift one pound (a full pint container) to the level of your shoulder without bending your elbow?
£
£
£
£
7
Can you lift eight pounds (a full gallon container) to the level of your shoulder without bending your elbow?
£
£
£
£
8
Can you carry twenty pounds at your side with this extremity?
£
£
£
£
9
Do you think you can toss a softball under-hand twenty yards with this extremity?
£
£
£
£
10
Do you think you can toss a softball over-hand twenty yards with this extremity?
£
£
£
£
11
Can you wash the back of your opposite shoulder with this extremity?
£
£
£
£
12
Would your shoulder allow you to work full-time at your regular job?
£
£
£
£
 F. A. Matsen

Matsen, F. A., 3rd, D. W. Ziegler, et al. (1995). "Patient self-assessment of health status and function in glenohumeral degenerative joint disease." J Shoulder Elbow Surg 4(5): 345-51.
One hundred three consecutive patients with primary glenohumeral degenerative joint disease completed standard questionnaires regarding their general health status (Short Form-36) and the function of their shoulder (Simple Shoulder Test). These patients' self-assessed health status indicated overall bodily pain, physical functioning, and physical role fulfillment scores that were significantly below those of population-based control groups. Self-assessed shoulder functions were likewise consistently below those of patients with normal shoulders. These deficits clearly indicated the problems that the patients desired to have resolved by treatment. The use of self-assessment questionnaires to routinely characterize patients with shoulder conditions is practical in the context of a busy practice. These data enable surgeons to understand the condition from the patient's perspective. This understanding should be central to the planning of treatment and to the evaluation of treatment effectiveness.


The simple shoulder test is responsive in assessing change following shoulder arthroplasty.


Responsiveness statistics are a useful means to compare different outcomes in terms of their ability to detect clinical change. While the responsiveness of the SST has been established for rotator cuff repair, it has not been determined for patients undergoing arthroplasty.


Patients undergoing shoulder arthroplasty (n=120) were evaluated prior to surgery and 6 months after. The evaluation included the SST, Disabilities of the Arm, Shoulder and Hand questionnaire, range of motion, and isometric strength. Responsiveness to change was assessed using standardized response mean (SRM), while longitudinal construct validity was evaluated using Pearson correlation. Receiver operating characteristics curves were plotted to determine clinically important difference of SST.

The SST and Disabilities of the Arm, Shoulder and Hand questionnaire were highly responsive (SRM, >1.70) for this population. For the assessment of impairment, range of motion (SRM, 0.64-1.03) was moderately to highly responsive, while isometric strength was minimally to moderately responsive (SRM, 0.32-0.69). The clinically important difference of the SST was established at 3.0 SST points. Pearson correlations indicated moderate associations between the change scores of the SST and the Disabilities of the Arm, Shoulder and Hand questionnaire (r=0.49).

The SST has been previously shown to be valid and highly reliable. The present results show that the SST is also responsive following shoulder arthroplasty and that it has a clinically important difference of 3.0 SST points. This should provide confidence to clinicians who wish to use a brief shoulder-specific measure in their practice.

=====
To see our new series of youtube videos on important shoulder surgeries and how they are done, click here.

Be sure to visit "Ream and Run - the state of the art"  regarding this radically conservative approach to shoulder arthritis at this link and this link. Also see the essentials of the ream and run.

Use the "Search" box to the right to find other topics of interest to you.


You may be interested in some of our most visited web pages   arthritis, total shoulder, ream and run, reverse total shoulder, CTA arthroplasty, and rotator cuff surgery